
iTechGuides is reader-supported. When you buy through links on our site, we may earn an affiliate commission. As an Amazon Associate I earn from qualifying purchases. Learn more
Safer coronary stents are designed to keep an artery open while reducing two major complications: restenosis, or renarrowing inside the treated segment, and stent thrombosis, a clot that can abruptly block the artery. Drug-eluting stents are recommended over bare-metal stents in the 2021 U.S. coronary revascularization guideline, but no design feature makes a stent universally safest. Outcomes also depend on the patient’s anatomy, the device’s approved use, and how well it is selected, sized, and implanted.
What a coronary stent is designed to do
A coronary stent is a small mesh tube placed in a narrowed heart artery during percutaneous coronary intervention (PCI). It props the vessel open to restore blood flow. A drug-eluting stent (DES) also releases medication over time to limit excess tissue growth that can narrow the treated area again. The American Heart Association’s patient guidance describes the role of stents and drug-eluting medication in these terms.
Keeping the artery open is not the only design goal. The device must also support healing of the vessel wall without provoking excessive tissue growth or a clot. Those aims can pull against one another: suppressing tissue growth helps prevent restenosis, while the vessel still needs to heal around the implanted structure.
Which complications safer design aims to reduce
Restenosis
Restenosis is the renarrowing of the artery within the treated segment. Tissue growth can contribute to it. Drug-eluting stents deliver an antiproliferative drug intended to limit that growth; changes to the metal platform, struts, and polymer coating have also been developed to improve vessel healing and reduce adverse events. These design approaches are not guarantees: restenosis remains a clinical problem despite improvements in stent technology, according to the Society for Cardiovascular Angiography & Interventions (SCAI) consensus statement on in-stent restenosis and stent thrombosis.
#1 Best Overall
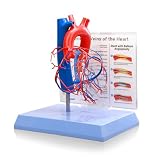
- Myocardial Circulation System: These arteries and veins are responsible for circulating blood to and from the myocardium, and the model also showcases two inserted stents
- Anatomical Blood Vessel Arrangement: The model illustrates the anatomical arrangement of the major blood vessels in a naturally sized heart, depicting the distribution of cardiac veins and coronary arteries encircling the exterior of the heart
- Atherosclerosis Demonstration: These narrow blood vessels are frequently impacted by atherosclerosis, leading to potential blockages that can result in angina or myocardial infarction
- Enhanced Coronary Anatomy: Features increased sized coronary anatomy that provides clear visualization of cardiac veins and arterial pathways for detailed study and examination
- Educational Display with Base: Life-size human heart model comes mounted on a sturdy base, making it suitable for classroom instruction, medical training, and anatomical reference purposes
Stent thrombosis
Stent thrombosis is a clot that blocks the stented artery. SCAI notes that it can close the artery abruptly and carries a high risk of myocardial infarction and death. It is distinct from restenosis, which is a gradual renarrowing. Both are reasons to consider device design and implantation quality together rather than treating the stent as a stand-alone safeguard.
How stent designs differ
Stent designs have changed in several interacting ways. A 2015 review traces development from stainless-steel platforms to cobalt or platinum-chromium alloys, along with changes to strut design, polymer coatings, and antiproliferative drugs. It discusses biocompatible and biodegradable polymers as well as polymer-free designs. That history describes directions in development, not a current ranking of individual products.
Rank #2
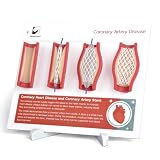
- PLAQUE & ARTERY NARROWING:Visualize coronary artery disease with detailed 3D artery sections showing plaque buildup and lumen narrowing, helping students and patients understand how atherosclerosis changes the vessel
- BALLOON & STENT DEMONSTRATION:See the angioplasty sequence with a catheter, balloon expansion and mesh stent placement. The side-by-side design makes key coronary intervention concepts easier to explain visually
- FOUR-STAGE VISUAL COMPARISON:Four artery models are arranged side by side for easy comparison of vessel narrowing, angioplasty and the expanded stent, helping simplify complex cardiovascular anatomy concepts
- CARDIOLOGY TEACHING AID:Designed for medical schools, nursing programs, anatomy classrooms, clinics and healthcare education, this coronary artery model supports cardiovascular and vascular anatomy instruction
- PATIENT EDUCATION DISPLAY:The freestanding labeled board keeps all four artery stages clearly visible during presentations, making it useful for doctor-patient communication, health education and clinical demonstrations
| Approach | Design purpose or evidence | Important qualification |
|---|---|---|
| Bare-metal stent (BMS) | A metal mesh platform without a drug-eluting coating. | The 2021 AHA/ACC/SCAI guideline recommends DES in preference to BMS during PCI to prevent restenosis, myocardial infarction, or acute stent thrombosis. |
| Drug-eluting stent (DES) | Releases medication intended to limit tissue growth and restenosis; platforms, strut geometry, polymers, and drugs vary. | Design features alone do not establish that one DES is safest for every patient or lesion. Use depends on clinical fit and device-specific indications. |
| Bioresorbable scaffold | Designed to provide temporary vessel support and then be absorbed. | A 2017 ESC-EAPCI task force found the Absorb scaffold had inferior outcomes to conventional DES at 2–3 years and advised against preferring it in practice at that time. That device-specific historical finding does not establish the safety of every future resorbable design. |
In the 2021 U.S. guideline slide set, the recommendation is stated as: “In patients undergoing PCI, DES should be used in preference to BMS to prevent restenosis, MI, or acute stent thrombosis.” This is a class-level recommendation over bare-metal stents, not an endorsement of one particular drug-eluting model.
Crashes, No Sound, or Screen Glitches?
Random freezes, missing sound and display glitches usually trace back to one bad driver. Find and replace yours safely.Free scan · under a minutePC Slower Than It Used to Be?
A free scan shows the junk files, broken settings and background clutter dragging Windows down - then fixes them in one click.Free scan · Windows 10 & 11What comparative evidence says—and what it does not
A 2016 network meta-analysis compared stent thrombosis across 147 trials involving 126,526 patients. At one year, the authors found lower definite or probable stent thrombosis with contemporary drug-eluting stents than with bare-metal and paclitaxel-eluting stents. They also found higher thrombosis risk with bioresorbable vascular scaffolds than with some contemporary drug-eluting stents.
Rank #3

- Anatomical Arrangement: The model illustrates the anatomical arrangement of the major blood vessels in a naturally sized heart, depicting the distribution of cardiac veins and coronary arteries encircling the exterior of the heart
- Blood Circulation System: These arteries and veins are responsible for circulating blood to and from the myocardium
- Atherosclerosis Demonstration: These narrow blood vessels are frequently impacted by atherosclerosis, leading to potential blockages that can result in angina or myocardial infarction
- Stent Visualization: The model also showcases two inserted stents for educational purposes
- Natural Size with Base: This vascular heart model comes in naturally large size and includes a stable base for display and study purposes
Those findings are tied to the devices, comparisons, endpoint, and one-year follow-up included in that analysis. They do not show that every newer device is safer than every older one, or predict an individual patient’s outcome. Longer-term performance and results in different lesion types require evidence specific to those devices and populations.
Why implantation technique matters as much as the device
A well-designed stent can still fail if its size or expansion is unsuitable for the artery, or if a procedural problem is missed. SCAI recommends intracoronary imaging at initial implantation to help minimize stent failure. Imaging can help clinicians understand the artery and assess stent placement; it complements rather than replaces appropriate device selection and procedural judgment.
Rank #4
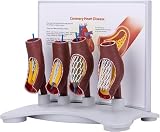
- Research reference: this vascular blockage replica recreates coronary stent features, supporting study of arterial occlusion and vessel intervention
- Clear teaching demo: this enlarged vessel model visually shows stent placement inside blocked arteries, helping learners understand vessel dilation procedures
- Premium material: made of eco-friendly pvc, this coronary stent model has sturdy structure and lifelike details; size 29x12x23cm for long-term display
- Anatomical training aid: this vascular stent model displays realistic vessel shapes and stent details, ideal for hands-on practice and anatomy learning
- Versatile use: suitable for school learning environments, works as a visual aid to help learners grasp human vascular structure
For patients, this means that “safer stent” is not only a question about the metal, drug, or coating. Relevant considerations include the lesion and vessel anatomy, the stent’s size and expansion, and whether imaging is used to guide implantation. These are clinical decisions for the interventional cardiology team, not features a patient can reliably evaluate from a product name alone.
The Tool Desk
Outbyte PC Repair FREEClear out junk files and repair common Windows errorsFree Scan →Outbyte Driver Updater FREEFix the driver behind crashes, sound loss and screen glitchesFind Drivers →How to assess a stent safety claim
When a device is described as safer, look for evidence that matches the claim rather than relying on a single design feature or the word “newer.” The useful questions are:
Best Value

- Cardiovascular System Model: GPI Anatomicals presents a model that shows an increased-size coronary anatomy depicting the cardiac veins and coronary arteries extending around the exterior of the heart. The model also illustrates an inserted stent.
- Anatomy Model: These arteries and veins, which circulate blood to and from the muscles of the heart, are commonly affected by atherosclerosis and can become blocked, causing angina or a heart attack. The model shows a dissected coronary occlusion as well.
- Model Specifications: This human anatomy model comes with an information card and a display base. The model measures 6.5" x 7.5" x 3", while the base measures 6.5" x 5". The dimensions of the information card are 8.25" x 6.25".
- Anatomy and Physiology Study Tools: A great substitute for anatomy posters, the model is perfect for display in a doctor's office or a healthcare facility for patient education. It can also be used as a teacher's accessory for classroom demonstrations.
- GPI Anatomicals: Our main focus is on prioritizing customer education. We offer different interactive models of the human body with utmost accuracy. Our models also make for one of the best gifts for medical students due to their informative nature.
- Which outcome was measured? Restenosis, repeat revascularization, myocardial infarction, and stent thrombosis are different outcomes.
- Which devices and patients were compared? Results depend on trial population, lesion complexity, comparator, and follow-up duration.
- What design feature is being discussed? Platform material, strut geometry, drug and release behavior, and polymer type or absence can differ, but a feature is not proof of a clinical advantage by itself.
- Does the device’s approved indication fit? Indications vary by device and jurisdiction. FDA labeling for a specific Resolute drug-eluting stent supplement warns that use outside specified indications may produce outcomes different from those in pivotal trials. That warning and its instructions apply to that labeling, not automatically to every stent.
- Was implantation guided and assessed appropriately? Device performance depends in part on fit, sizing, expansion, and procedural technique.
What patients can ask their cardiology team
Questions about a planned PCI can make the design and procedural trade-offs clearer without assuming that one stent category is right for everyone:
- Why is this stent type appropriate for my artery and lesion?
- What outcomes or risks are most relevant in my case?
- How will the team assess the stent’s size and expansion during the procedure?
- Will intracoronary imaging be used to guide implantation, and why or why not?
- Are there device-specific indications or limitations that apply to my situation?
The 2021 guideline provides a clear U.S. recommendation favoring drug-eluting over bare-metal stents during PCI. Device selection and implantation still need to be tailored to the clinical situation, and the evidence for any newer or resorbable design should be judged on its own outcomes rather than on its engineering concept alone.
Quick Recap
Product prices and availability are accurate as of the date/time indicated and are subject to change. Any price and availability information displayed on Amazon at the time of purchase will apply.

